
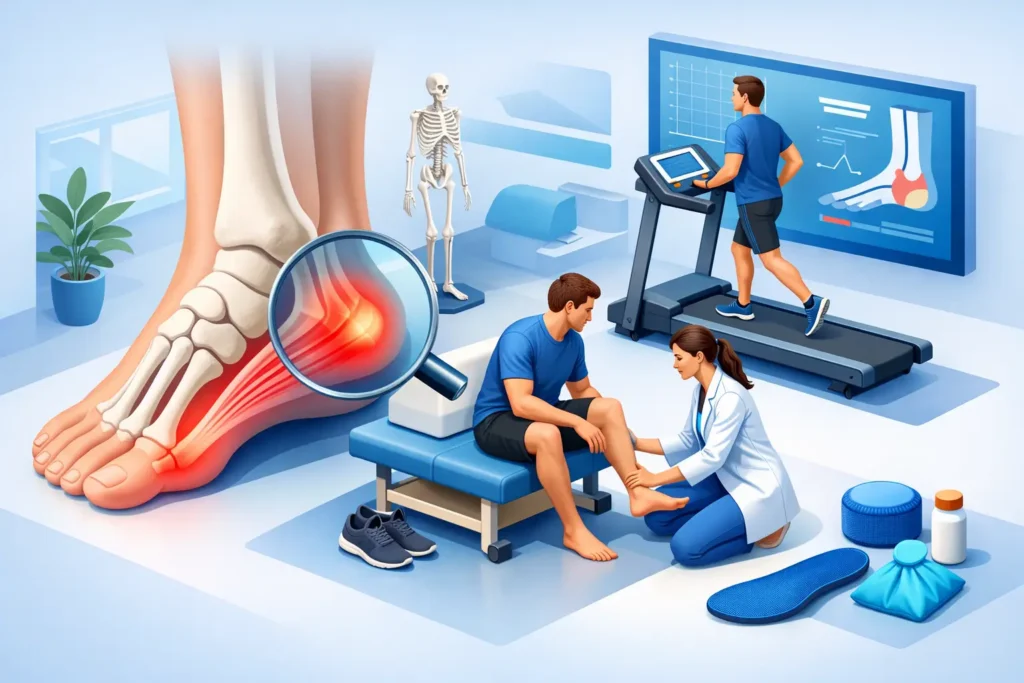
The pain was most severe on the first few steps out of bed. By the time this patient reached the office, it had often eased – only to return after a long meeting, a commute home, or a weekend walk. In this case study of chronic plantar fasciitis, we look at why persistent heel pain needs more than generic stretching advice, and how a clear, evidence-based plan can help restore confident movement.
This is a representative clinical case based on common presentations seen in specialist musculoskeletal practice. Individual symptoms, diagnoses and treatment recommendations always require a full assessment.
When heel pain stops being a minor problem
Our patient was a 46-year-old working professional who enjoyed running, gym sessions and walking around London. Heel pain had begun gradually around nine months earlier, without one clear injury. Initially, it was manageable: discomfort on getting out of bed, then a sharp pull under the heel after sitting for a while.
Over the following months, the problem became more limiting. Running stopped, daily step counts dropped, and standing for longer periods became difficult. The patient had tried supportive trainers, online stretches, over-the-counter insoles and anti-inflammatory medication. These measures offered short-lived relief but did not address the underlying problem.
This pattern is common. Plantar fasciitis is often described as inflammation of the plantar fascia, the strong band of tissue running from the heel into the arch of the foot. In longer-standing cases, however, the issue may be less about active inflammation and more about pain sensitivity, reduced tissue capacity and changes within the fascia itself. That distinction matters because the best treatment plan for persistent symptoms is rarely just rest.
Assessment: looking beyond the painful spot
The first priority was to confirm the source of pain and identify what was continuing to load the area. A specialist assessment considered the location and behaviour of symptoms, footwear, training history, work demands, ankle movement, calf strength, foot mechanics and walking pattern.
The patient had marked tenderness at the inside edge of the heel, where the plantar fascia attaches. Ankle dorsiflexion was restricted, meaning the ankle did not move sufficiently over the foot during walking. The calf was also weaker than expected for the patient’s activity level. This combination can increase the pull through the plantar fascia with every step.
Diagnostic ultrasound provided fast, accurate insight. It showed thickening and altered fibre appearance at the plantar fascia insertion, consistent with chronic plantar fasciopathy. There was no sign of a plantar fascia tear. The scan also helped rule out other potential contributors, such as a heel fat-pad problem or a nearby tendon condition.
Not every patient with heel pain needs imaging. A straightforward, recent presentation may respond well to a clinical assessment and conservative care. Ultrasound becomes particularly useful when pain has persisted, progress has stalled, the diagnosis is uncertain, or an injection or shockwave treatment is being considered.
Why the diagnosis can be missed
Pain beneath the heel is not always plantar fasciitis. Nerve irritation, stress injury, inflammatory arthritis, referred pain from the back, tendon problems and a bruised heel pad can create similar symptoms. A good assessment does not simply confirm the most likely diagnosis. It checks for the details that would change treatment.
In this case, there was no night pain, numbness, unexplained swelling, systemic illness or history suggesting an inflammatory condition. If these features are present, further medical investigation may be required before starting a rehabilitation programme.
The treatment plan for chronic plantar fasciitis
The patient’s plan combined symptom management with progressive loading. The aim was not to chase a completely pain-free foot from day one. It was to settle irritability, improve how the foot and calf tolerated load, and build a return to normal activity without repeated flare-ups.
Reducing the strain without stopping life
The first two weeks focused on practical changes. The patient paused running and hill walking but continued low-impact exercise, including cycling. We advised avoiding barefoot walking on hard floors, especially first thing in the morning, and reviewed footwear to ensure adequate cushioning and support.
A temporary heel lift and prefabricated orthotic were used to reduce tension through the plantar fascia. These tools can be helpful, but they are not a cure in themselves. Some people gain significant relief; others find little difference. The key is to use them as part of a broader plan rather than relying on them indefinitely.
Targeted manual therapy and soft-tissue work were used to improve comfort and ankle movement. The patient was also shown how to perform a specific plantar fascia stretch before taking the first steps of the day. This was short, manageable and fitted around a working schedule.
Building capacity through rehabilitation
Once morning pain had begun to settle, the emphasis moved towards strength. Calf and foot muscles help manage the forces travelling through the plantar fascia, particularly during walking, stair climbing and running.
The programme began with controlled calf raises and progressed to heavier, slower resistance work. Foot-strengthening exercises, balance drills and mobility work were added according to tolerance. Each exercise had a clear purpose: not simply to make the foot work harder, but to improve the capacity of the entire lower leg to absorb daily load.
Pain monitoring was essential. Mild discomfort during exercise can be acceptable in chronic tendon and fascia rehabilitation, provided it settles promptly and does not lead to worse first-step pain the next morning. Sharp pain, limping or a sustained increase in symptoms means the programme needs adjusting.
When shockwave therapy was added
After several weeks, the patient had improved but still experienced stubborn pain after longer walks. As ultrasound findings and symptom duration supported a chronic plantar fasciopathy diagnosis, extracorporeal shockwave therapy was introduced alongside rehabilitation.
Shockwave therapy uses acoustic waves to stimulate a healing response in persistently painful tissue. It is not a quick fix, and it can be uncomfortable during treatment. However, for appropriately selected patients whose symptoms have not settled with initial conservative care, it can be a valuable non-surgical option.
At FAB Clinic, this decision would be made within an integrated plan – combining specialist assessment, imaging-led diagnosis and rehabilitation rather than treating shockwave as a standalone answer. The exercises and activity progression remain central to longer-term recovery.
The outcome: gradual progress that held
By week six, first-step pain had reduced substantially and the patient could stand through work commitments without planning every break around heel discomfort. At week 10, longer walks were comfortable again, and a graded return-to-run programme began.
The return to running was deliberately cautious. Rather than testing the foot with one ambitious weekend run, the patient started with short run-walk intervals on level ground, with rest days between sessions. Distance and pace increased only when morning symptoms remained stable.
At the three-month review, the patient had returned to regular exercise and was managing a normal working day without heel pain dictating choices. There were occasional mild symptoms after unusually busy days, but the patient understood how to respond: reduce load briefly, maintain strength work and avoid abandoning the plan at the first sign of discomfort.
What this chronic plantar fasciitis case study shows
Persistent plantar heel pain is frustrating because it affects ordinary moments as much as sport. It can make getting out of bed difficult, turn a walk to the station into a calculation, and gradually reduce the activity that supports health and wellbeing.
The practical lesson is that chronic plantar fasciitis usually improves most reliably when treatment matches the person, not just the diagnosis. Accurate assessment can identify whether the plantar fascia is truly the pain source. Imaging can clarify stubborn cases. Rehabilitation rebuilds tolerance. Treatments such as shockwave therapy may provide an additional route forward when the condition has not responded to basic measures.
If heel pain has lasted for months or keeps returning whenever you become more active, do not assume you simply need to stretch harder. A specialist assessment can provide the clarity and structured recovery plan needed to keep you moving with greater comfort and confidence.